
Psoriasis affects about 2% of people in France, and it is far more than red, flaking patches on the skin. This chronic inflammatory disease sends signals into the bloodstream that also reach the arteries. Large British and American cohorts link psoriasis to more heart attacks, strokes and high blood pressure, especially in severe forms and in younger patients. The link is solid, but it is partly explained by shared risk factors such as excess weight and smoking. Here is what science has established, what it still does not know, and the habits that protect the heart.
In brief – Psoriasis is a chronic inflammatory skin disease whose inflammation circulates throughout the body and speeds up wear on the arteries. According to Inserm, France’s national health research institute, it raises cardiovascular risk by about 25%, independently of classic risk factors. A meta-analysis of 9 studies (218,654 patients) links the severe form to a 1.70-fold risk of heart attack and to 39% higher cardiovascular mortality. In a 30-year-old patient with a severe form, the relative risk of heart attack reached 3.1 in the Gelfand cohort (2006). Affected patients also have more hypertension, more metabolic syndrome and more non-calcified coronary plaque. No trial has yet proven that treating the skin reduces heart attacks. The practical priority: screen blood pressure, cholesterol and blood sugar, and act on weight, smoking and physical activity.
Psoriasis: definition of a systemic inflammatory disease
Psoriasis is defined as a chronic, non-contagious inflammatory disease that mainly shows up as thick red plaques covered with white scales. In France, it affects about 2% of the population and is complicated by joint pain (psoriatic arthritis) in 20% of cases. As the NHS guide to the condition explains, the plaque form remains the most common.
Worldwide, an analysis of 168 studies published in the BMJ puts prevalence at 1.92% in Western Europe, compared with 0.14% in East Asia (Parisi et al., 2020). The WHO global report on psoriasis ranks it among serious noncommunicable diseases and highlights the increased risk of cardiovascular disease in people who have it.
Dermatologists now speak of “psoriatic disease”: the skin involvement is only the visible part of an inflammation that also affects the joints, metabolism and blood vessels.
How psoriasis inflammation reaches the heart and arteries
The disease sustains low-grade inflammation throughout the body, and this inflammation promotes atherosclerosis, the thickening of artery walls by plaque. The same immune messengers act in the skin and in the arterial wall. Researchers at the US National Institutes of Health (NIH) describe the condition as a human model of “inflammatory atherosclerosis”.
Several mechanisms combine:
- Pro-inflammatory cytokines (TNF-alpha, interleukin-17, interleukin-23, interleukin-6) enter the circulation and activate the cells of the artery wall.
- Neutrophils, a type of white blood cell, are more numerous and more activated; their protein S100A8/A9 was almost four times higher in 60 patients than in 20 controls.
- Insulin resistance and abdominal fat, both more frequent with the disease, add their own inflammation.
- Chronic stress, depression and poor sleep, common among patients, also weigh on blood pressure.
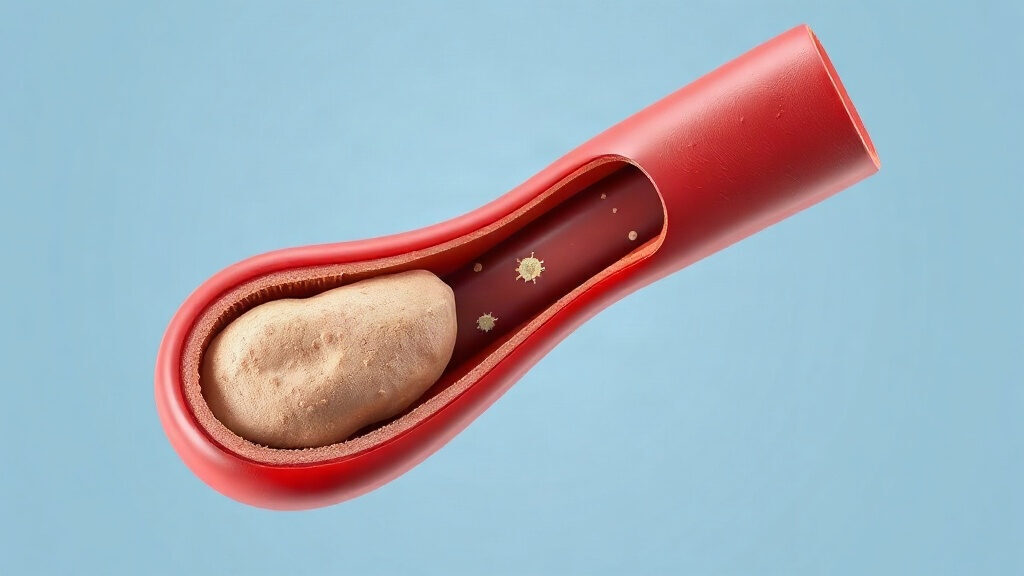
Imaging confirms this link. In a prospective study, the larger the skin area affected, the stronger the aortic inflammation measured by PET scan (β = 0.41), independently of age and Framingham score (Naik et al., 2015). This mechanism matches that of age-related chronic inflammation, one of the drivers of cardiovascular aging.
Psoriasis and heart risk: what the science says
Population studies show an excess of heart attacks, strokes and cardiovascular deaths in people with psoriasis, and the excess grows with severity. The first major warning came from a British cohort of 130,976 patients followed for 5.4 years on average. After adjusting for blood pressure, diabetes, cholesterol, smoking and body mass index, the relative risk of heart attack reached 3.10 at age 30 with a severe form, and 1.36 at age 60 (Gelfand et al., 2006).
The same team then studied mortality. Among 3,603 patients on systemic treatment, the risk of cardiovascular death was 57% higher (HR 1.57), or one extra cardiovascular death per year for every 283 patients (Mehta et al., 2010). The meta-analysis of 9 studies confirms the trend and estimates the excess at 11,500 major cardiovascular events per year in the United States (Armstrong et al., 2013).
| Event | Mild form | Severe form |
|---|---|---|
| Heart attack (myocardial infarction) | RR 1.29 | RR 1.70 |
| Stroke | RR 1.12 | RR 1.56 |
| Cardiovascular mortality | Not established | RR 1.39 |
Classic risk factors are also more frequent. Across 24 studies and 309,469 patients, the odds of hypertension were 1.58 times higher than in the general population (Armstrong et al., 2013). Among 4,065 British adults aged 45 to 65, metabolic syndrome followed a dose effect: odds ratio 1.22 when 2% of body surface or less was affected, 1.98 above 10% (Langan et al., 2012).
Coronary CT scans provide the most direct evidence. In 105 young, low-risk patients, the burden of non-calcified plaque, the most unstable kind, exceeded that of hypercholesterolemic patients about 10 years older (Lerman et al., 2017). These data remain observational: a solid association, not proof of causation in the strict sense.
In practice: does treating psoriasis protect the heart?
No randomized trial has yet shown that treating the skin disease reduces heart attacks or strokes. The available data concern intermediate markers (imaging, blood tests), and they partly contradict each other. The table below summarizes the main results.
| Study | Type | Main result |
|---|---|---|
| Lerman 2017 (50 patients) | Observational, 1 year | Skin improvement associated with less non-calcified plaque |
| Elnabawi 2019 (134 patients) | Observational, 1 year | Lower coronary inflammation with biologic therapy, not without it |
| Mehta 2018, VIP trial (97 patients) | Randomized, placebo-controlled | No effect on aortic inflammation; CRP and IL-6 decreased |
| González-Cantero 2021 | Meta-analysis of trials | Effects mainly on blood markers; clinical events not assessed |
In the Oxford and NIH study, 82 patients on biologic therapy saw their coronary inflammation decrease within a year, unlike the 52 treated with creams or phototherapy (Elnabawi et al., 2019). But the more rigorous randomized VIP trial found no difference in aortic inflammation after 12 and 52 weeks of adalimumab, despite a drop in CRP and IL-6 (Mehta et al., 2018). The 2021 meta-analysis concludes that trials measuring cardiac events are still needed (González-Cantero et al., 2021).
The longevity reading: controlling the disease well remains desirable for quality of life, but the proven cardiac lever runs through the classic risk factors. Choosing a treatment is a matter for the dermatologist. To put your own numbers in context, see our benchmarks on the blood pressure number to watch. The topic belongs to our pillar on altered intercellular communication, which gathers our articles on inflammation.
Psoriasis: 7 habits to protect your heart
The first step is to have your cardiovascular risk factors measured regularly, because they are more frequent and often under-screened in these patients. The following advice draws on the studies cited and on general prevention guidelines.
- Check your blood pressure at least once a year, and more often if a treatment such as ciclosporin is prescribed.
- Test cholesterol, triglycerides and fasting blood sugar, especially with an extensive form or a systemic treatment.
- Aim to lose weight if you are overweight: in a Danish trial of 60 patients, losing 15.4 kg (34 lb) in 16 weeks improved diastolic blood pressure, cholesterol, triglycerides and blood sugar (Jensen et al., 2014).
- Quit smoking, which worsens both the skin lesions and the risk of heart attack.
- Limit alcohol, which is associated with flare-ups and liver damage.
- Move at least 150 minutes a week at moderate intensity, as the WHO recommends for all adults.
- Tell your primary care doctor about your diagnosis so they can factor it into your overall cardiovascular risk assessment.
The same Jensen trial also showed better skin-related quality of life after weight loss, with a trend toward improvement of the plaques (Jensen et al., 2013). On the diet side, regular servings of oily fish and vegetables fit general heart-health guidelines; our article on chronic inflammation and its levers details the habits that lower inflammatory markers.
Frequently asked questions about psoriasis and the heart
Why does psoriasis increase cardiovascular risk?
Psoriasis releases inflammatory molecules into the blood (TNF-alpha, interleukin-17, interleukin-6) that also act on the artery wall and promote atheromatous plaque. On top of this come risk factors that are more frequent in patients: excess weight, hypertension, metabolic syndrome and smoking. France’s Inserm estimates the excess risk at about 25%, independently of classic factors.
Does mild psoriasis also put the heart at risk?
Yes, but moderately. In the 2013 meta-analysis, mild psoriasis was associated with a 29% higher risk of heart attack and a 12% higher risk of stroke. Severe forms, treated with systemic drugs, show a more marked excess: a 1.70-fold risk of heart attack and 39% higher cardiovascular mortality.
What tests should you have if you have psoriasis?
A basic cardiovascular checkup is enough in most cases: blood pressure, waist circumference, weight, lipid panel and fasting blood sugar. Your primary care doctor can include it in your annual follow-up. With an extensive form, associated arthritis or a family history, they may suggest further tests depending on your risk profile.
Do biologic therapies for psoriasis protect the heart?
This has not been demonstrated. Observational studies associate biologics with less coronary inflammation, but the randomized VIP trial found no effect of adalimumab on aortic inflammation after 52 weeks. No trial has yet measured the effect on heart attacks. The choice of treatment is made with the dermatologist, based on the severity of the disease.
Does losing weight improve psoriasis?
In overweight patients, losing weight mainly improves the cardiovascular profile. In a Danish trial of 60 patients, an average loss of 15.4 kg (34 lb) in 16 weeks reduced diastolic blood pressure, cholesterol, triglycerides and blood sugar. Skin-related quality of life also improved, with a favorable trend in the extent of the plaques.
Medical disclaimer. The information on this page is provided for informational purposes only and does not constitute medical advice. It does not replace a consultation. Never stop or change a psoriasis treatment without your dermatologist’s advice. If you have chest pain, unusual shortness of breath or palpitations, seek care immediately or call your local emergency number (911 in the US, 999 in the UK, 112 in Europe). Ask a healthcare professional before changing your diet, taking dietary supplements or starting a new practice, especially if you have a medical condition, are pregnant or are under treatment.


